
What is the best peptide for joint pain?
For most people, oral collagen. UC-II (40 mg a day) beat placebo and glucosamine plus chondroitin in a 191-person knee osteoarthritis trial. Hydrolyzed collagen cut knee pain in a 507-patient meta-analysis. BPC-157 has the best animal data, but its only knee study is a 16-patient chart review. If weight is part of the problem, semaglutide has the biggest joint-pain trial of any peptide.
Updated September 2026: added semaglutide and two 2025 collagen trials, corrected how the BPC-157 knee study is described, and updated BPC-157’s FDA status after the April and July 2026 changes.
It’s based on two things. The actual problem with the joint and desire for injection.
Strongest human evidence: UC-II collagen at 40 mg a day, and hydrolyzed collagen at 3 to 10 g a day used in the knee trials. Oral, cheap, legal and randomized trials have supported.
Best for one particular injured joint: BPC-157 typically paired with TB-500. Promising rat studies. The human data is one of 16 patients who are not in the placebo group.
Semaglutide is the GLP1 peptide used in Wegovy and it is the largest trial of any peptide for the treatment of joint pain. Study participants were 407 people with obesity and knee osteoarthritis, for 68 weeks. If weight is an issue, relevant.
If you’ve heard that BPC-157 can cure everything and you’re knee joints crack in the stairs, read this before you go out and buy a vial. That signature 91.6% success rate? Wait until you can determine its source.
The majority of people think that the injectable research peptides are the “real deal” and collagen is the “grocery store” version. It’s more like the other way round.
Peptides are short chains of amino acids, which are like biological text messages. Peptides try and guide cells in what to do, rather than mask pain or pour raw materials into a joint and pray it will work. Repair a tissue. Recruit blood vessels. To control an inflammatory pathway.
Peptides for Joint Pain Compared: The Human Evidence at a Glance
Here is the whole field on one screen. “People studied” means the size of the best human study for joint pain. Animal and lab studies don’t count here.
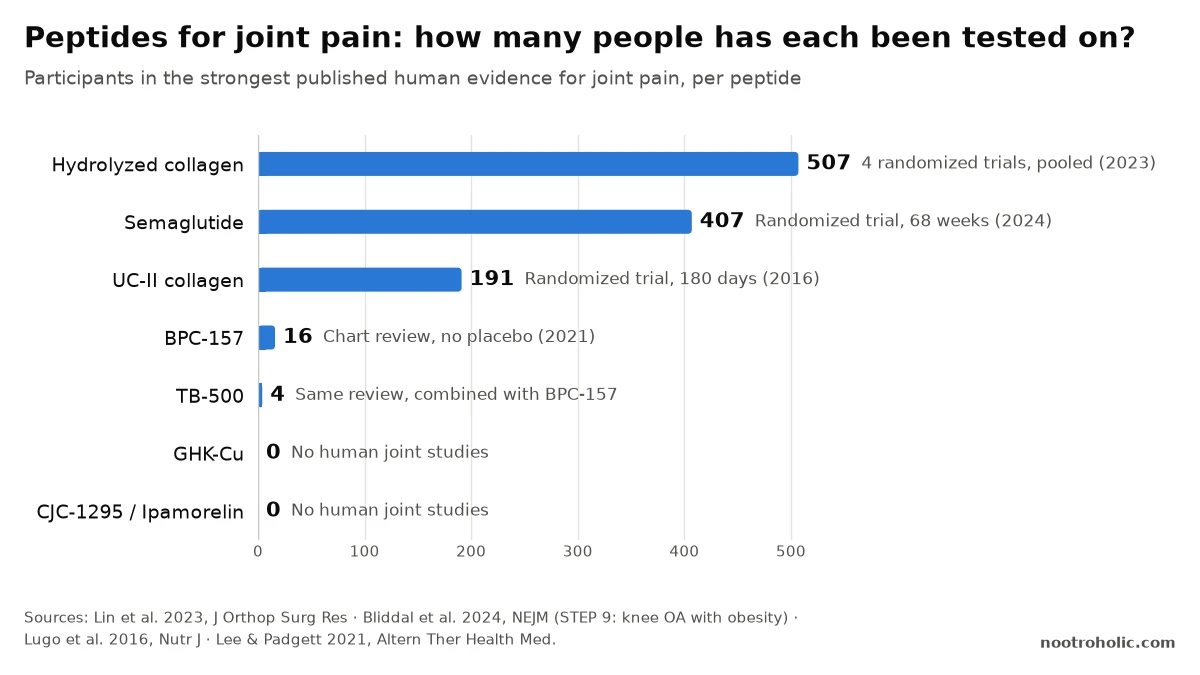
| Peptide | Best human evidence | People | Dose and route | US status (Sep 2026) |
|---|---|---|---|---|
| UC-II collagen | RCT vs placebo and glucosamine, 180 days | 191 | 40 mg/day, oral | Supplement |
| Hydrolyzed collagen | Meta-analysis of 4 RCTs | 507 | 6.8 to 10 g/day, oral | Supplement |
| Semaglutide | RCT, 68 weeks, obesity + knee OA | 407 | 2.4 mg weekly, injection | Prescription |
| BPC-157 | Chart review, no placebo | 16 | Not standardized, injection | Unapproved, compounding pending |
| TB-500 | Same review, with BPC-157 | 4 | Not standardized, injection | Unapproved, compounding pending |
| GHK-Cu | None for joints | 0 | None | Unapproved |
| CJC-1295 / Ipamorelin | None for joints | 0 | None | Unapproved |
Peptide Injections for Joint Pain: Do You Actually Need Them?
It’s the question that you are looking at in most of your search of this topic. The answer for most people suffering with joint pain is no, and the focus is sure to be on the injectable peptides for joint pain. There is better evidence for oral peptides for joint pain.
Collagen peptides are taken orally. Both UC-II and hydrolyzed collagen act in the gut. No needles, no gray market vendor, no reconstitution. All collagen trials mentioned on this page were given a dose orally.
BPC-157, TB-500 and GHK-Cu are almost always injected, since their oral bioavailability (how well they are absorbed into the bloodstream) for joint use is either not known or is poor. In practice there are two routes.
- Subcutaneous. In the fat tissue, typically around the affected joint. Almost all of the online peptide injection protocols for knee pain are formulated like this.
- Intra-articular. Immediately into the joint capsule. A clinical rather than a kitchen-table procedure. The 16-patient BPC-157 knee review below used this route, given by clinicians.
A research-grade peptide injected into the joint capsule has an infection risk which a shot under the skin does not. Joints lack a good blood supply. Septic arthritis is a medical emergency. It is not a side effect that you’ll have to endure.
So the honest order for most people. Start oral, because the evidence is better and the risk is close to zero. Move to injectable peptides only if a full 8 to 12 week oral run has not shifted anything. Leave intra-articular injections to a clinician. And check where BPC-157’s legal status stands in 2026 before you buy anything.
So which peptides actually earn a spot? Here are all 7, with the evidence next to each one.
The 7 Best Peptides for Joint Pain (and How Strong the Evidence Really Is)
I have included them in the order they are asked in. For the ranking by evidence, use the table above. Each peptide receives two grades, where appropriate. One for animal and lab data and one for human data. It’s at BPC-157 where the two grades are the furthest apart.
#1. BPC-157
Evidence Rating: A- for animal data, D for human data (Large and consistent animal literature. One small uncontrolled human knee look over. Huge anecdotal foundation.)
The most popular used when people ask about peptides for joint repair. It was also the first peptide to be considered by the FDA’s compounding advisory committee in July, 2026.
Ignore the hype, for today. What are the findings of the research?
BPC-157 is a 15 amino acids peptide first isolated from human gastric juice. A great deal of animal research is positive and large. Stimulates new blood vessels (angiogenesis). This is important because impaired joints and tendons lack blood. Animal studies reaveal it stimulates growth hormone receptors and effects nitric oxide pathways to promote faster tissue repair.
February 2026 review looked at BPC-157 in tendon, ligament and muscle injury. Animal model results were consintently positive with regard to tendon, ligament and bone healing. The peptide accelerated the repair of the Achilles tendon in rats, enhanced fracture repair and reduced inflammatory markers in joint tissue. Proper clinical trials in humans are still lacking, as the same review say.
The Human Data So Far
The only knee study is a retrospective chart review published in 2021. The 16 patients contacted by phone experienced less knee pain with BPC-157 intra-articular administration in 11 of the 12 patients. Now, that is the quoted 91.6% you see everywhere. It is 11 people that respond to a phone call. No placebo group and no validated pain scale. The majority of patients self-assessed the pain 6-12 months after the injection.
The only other human data is a 2025 safety pilot in 2 healthy adults. They took up to 20 mg intravenously, and nothing measurable changed in their heart, liver, kidney, thyroid or blood sugar markers. A promising signal. Not proof. I think BPC-157 is worth watching, but not yet worth betting a knee on. For the full breakdown, see our BPC-157 research guide.
#2. TB-500 (Thymosin Beta-4) and the Wolverine Stack
Evidence Rating: B+ for animal and equine data, D for human data (Strong animal data for tissue repair, extensive equine use, 4 human patients)
BPC-157 sends repair signals. TB-500 push the repair team. It’s a piece of a protein present in nearly all cells. Assists cells to move to damaged tissue and develop into the tissue’s cells. Reduces inflammation and down regulates adhesion molecules to prevent scars after injury.
Used for years by racehorse vets to treat tendon injuries, muscle tears and joint inflammation. The data from the horses is consistent and positive. However, you’re not a horse.
TB-500 focus on chronic inflammation and structural damage. BPC-157 is a single-site drug. Effect are on the body-wide inflammation which prevents joint healing. Hence, why it’s on the list of peptides for joint pain and inflammation. Frequently used in combination by researchers.
The Wolverine Stack (BPC-157 + TB-500 Combined)
The most popular peptide stack for joint pain, in biohacking forums and wellness clinics. The logic is simple. BPC-157 handles the repair signal at the injury, and TB-500 handles inflammation and cell migration. Together they cover both sides of healing. We compare the two head to head in BPC-157 vs TB-500.
No controlled trial on this combination. The only published human data is 4 patients in the same 2021 knee review, and 3 of them reported relief. Everything else comes from user reports, which are many and consistent.
If you’ve searched “what are the 3 peptides for joints”, this is usually the answer. It’s the pre-mixed “GLOW” blend of BPC-157, TB-500 and GHK-Cu that several peptide vendors sell.
#3. GHK-Cu (Copper Peptide)
Evidence Rating: B for lab data, no human joint data (Solid mechanistic data, good in-vitro evidence, no joint trials in people yet)
GHK-Cu is not the obvious choice. BPC-157 and TB-500 gets the spotlight. But the lab data on copper peptides for joints is some of the most interesting on this page.
GHK-Cu is a tripeptide, just 3 amino acids bound to a copper ion. Your blood already has it. Levels drop from roughly 200 ng/mL at age 20 to about 80 ng/mL by age 60, and tissue repair slows down over the years.
This peptide boosts collagen synthesis and glycosaminoglycan production. Those are the molecules that keep cartilage springy. Calms inflammation through the TGF-beta and metalloproteinase pathways.
What makes GHK-Cu interesting for joint health is the remodelling of tissue instead of just patching it. Lab studies show it can attract immune cells, grow new blood vessels and stimulate nerve growth. So in theory it could work on the structural damage of osteoarthritis and not only the pain. Few peptides for cartilage repair works like GHK. In theory. Nobody has tested it in human joints yet.
Injectable GHK-Cu was one of the 12 peptides the FDA took off its Category 2 list in April 2026. If you still want to try it, our guide to where to buy GHK-Cu covers which vendors pass testing.
#4. Hydrolyzed Collagen Peptides (Types I & III)
Evidence Rating: A- (Multiple human RCTs, meta-analyses, well-established safety profile)
Here’s something that surprised me. Hydrolyzed collagen peptides have stronger human clinical evidence than BPC-157 for joint pain. The gap between hype and evidence is inverted. BPC-157 gets all the attention. Collagen has more human trials.
If collagen isn’t in your routine yet, you’re leaving the best-studied option on the shelf. It runs $30-60 a month against $200-400 for a BPC-157 and TB-500 cycle, and you never touch a needle.
Hydrolyzed collagen is regular collagen broken down into small peptide fragments. They survive digestion, enter the bloodstream and build up in cartilage. And they do more than supply building blocks. Research shows they push the cells that make cartilage and connective tissue to produce more of their own collagen. So the collagen you eat sends a signal to make more collagen. We cover what else supports that process in which supplements help collagen production.
The Dose Matters More Than Brand
If you’re hunting for the best collagen peptides for joints, the dose matters more than the brand. A 2023 meta-analysis pooled 4 randomized trials with 507 knee osteoarthritis patients. At 6.8 to 10 g a day for 6 to 24 weeks, collagen reduced pain more than placebo. Side effects were not statistically different between the groups. A 2025 Korean trial found a small benefit at just 3 g a day over 180 days, at the low edge of what patients notice. Give it at least 8 to 12 weeks.
If you’re underdosing, you’re wasting money.
Check the grams per serving on the label and do the math against the trial doses. One small scoop often isn’t enough.
Source matters too. Bovine collagen is the most studied for joints. Marine collagen is popular, but almost nobody has compared the two for joint pain.
#5. UC-II (Undenatured Type II Collagen)
Evidence Rating: A (The strongest human evidence of any collagen type for joint pain)
Hydrolyzed collagen provides building blocks and signaling fragments. UC-II works in a completely different way. It’s called oral tolerance.
A small daily dose of undenatured type II collagen in your gut trains your immune system to stop attacking your own joint cartilage.
Why does it matter?
Because in osteoarthritis, and even more in rheumatoid arthritis, the immune system helps destroy cartilage. UC-II calms that response down.
The key trial randomized 191 people with knee osteoarthritis for 180 days. Just 40 mg of UC-II a day beat placebo. It also beat 1,500 mg glucosamine plus 1,200 mg chondroitin on WOMAC, the standard score for knee pain, stiffness and function. Glucosamine plus chondroitin didn’t even beat placebo.
Forty milligrams beats fifteen hundred milligrams of the old gold standard. A 2025 review of the UC-II research reached the same conclusion, but noted the trials were small and short.
One caution, and I’d rather you hear it from me. That 191-person trial was paid for by the company that makes UC-II. In 2025 an independent Thai trial gave 68 people a low-dose combo of 20 mg UC-II and 480 mg hydrolyzed collagen for 12 weeks. It did no better than placebo. So dose matters. Use the doses that were actually tested.
Here’s the key thing about collagen types for joints. UC-II at 40 mg works through the immune system. Hydrolyzed collagen at several grams works through structure and cell signaling. They do different jobs. So for many people, 40 mg of UC-II plus a full dose of hydrolyzed collagen covers both.
UC-II Dosing
40 mg daily. That’s the dose the trials tested, and there’s no evidence that more works better. The main trial measured its results at 180 days, so give it time. Look for brands using the patented UC-II ingredient with clinical validation.
#6. Semaglutide (If Your Weight Is Loading the Joint)
Evidence Rating: A for knee osteoarthritis in people with obesity (Large, 68-week randomized trial in a top journal. Prescription only.)
Nobody thinks of it as a joint peptide. It has the biggest joint-pain trial on this page anyway.
Semaglutide is a GLP-1 peptide, the active ingredient in Wegovy. In the STEP 9 trial (New England Journal of Medicine, 2024), 407 adults with obesity and knee osteoarthritis took 2.4 mg once a week or placebo for 68 weeks, alongside diet and exercise counseling. WOMAC pain scores fell by 41.7 points on semaglutide versus 27.5 on placebo. Body weight fell 13.7% versus 3.2%. SF-36 physical function scores improved by 12.0 points versus 6.5.
That is more people, followed for longer, than every human BPC-157 study put together.
The limits are just as clear. It is a prescription drug. STEP 9 only enrolled people with obesity, so it tells you nothing about a lean athlete with a sore tendon. And 6.7% of people on semaglutide quit because of side effects, mostly stomach problems. On placebo it was 3.0%. If your knees hurt and your weight is high, talk to your doctor about it. A peptide vendor can’t help you here.
#7. Growth Hormone Secretagogue Peptides (CJC-1295/Ipamorelin, AOD-9604)
Evidence Rating: C+ (Indirect joint benefits through growth hormone pathways. Little joint-specific data.)
These don’t target joints directly. They stimulate your body’s growth hormone (GH) production, which has downstream effects on tissue repair, collagen synthesis and recovery.
CJC-1295 combined with Ipamorelin is the most popular GH secretagogue stack in the anti-aging and performance communities.
I’m ranking them last because the joint benefits are indirect and the evidence is thin. But growth hormone affects every connective tissue in your body. So if your joint pain comes from recovery slowing down in general, which is common after 40, working on GH can help.
AOD-9604 is a modified fragment of human growth hormone originally studied for fat metabolism. It’s gained attention in the joint space because of its anti-inflammatory properties and some evidence of cartilage repair in animal models.
One to Watch: TPX-100
This is what a joint peptide looks like when someone actually runs the trials. TPX-100 is a 23-amino-acid peptide being developed for knee osteoarthritis. In a Phase 2 study, each patient got TPX-100 injected into one knee and placebo into the other. At 12 months, treated knees showed 26% better WOMAC function and less damaging change in bone shape. You can’t buy it. But it’s the bar the research-chemical peptides haven’t cleared yet.
Which Peptide Is Right for Your Joint Pain? Osteoarthritis, Knee, RA and Tendons
Your best option depends on 3 things. What’s causing the pain, how much risk you accept, and your budget.
Best Peptides for Osteoarthritis (Mild to Moderate)
If you want the best peptide for osteoarthritis on the evidence, start with UC-II collagen (40 mg daily) plus hydrolyzed collagen (around 10 g daily). This combo works on both the immune attack on cartilage and the structural collagen decline. It’s legal, affordable ($40-60/month), backed by human trials, and has almost no side effects.
Use full doses. The one trial that tested a low-dose combo found nothing. Give it 90 days before you judge it. If your weight is high, ask your doctor about semaglutide, which has the biggest osteoarthritis trial of any peptide. If you’re still stuck after that, some people add BPC-157 injections under the skin near the joint.
We go deeper on peptides for arthritis pain, including what people in remission use, in a separate guide.
If You’re Recovering from a Sports Injury or Surgery
The Wolverine Stack (BPC-157 + TB-500) is what most biohackers and athletes reach for first. BPC-157 works on repair at the injury site. TB-500 lowers inflammation and moves repair cells in. Add hydrolyzed collagen (around 10 g daily) so your body has the raw material to rebuild. Expect to pay $200-400/month for 8-12 weeks. Our guide to peptides for injury recovery covers the protocols in detail.
If you compete in a tested sport, stop here. BPC-157 and TB-500 are both on the WADA prohibited list, banned in and out of competition, with no therapeutic use exemption available. Athletes have received four-year bans for them.
If You’re Over 50 with General Joint Stiffness
If you just want peptides for joint health as you age, start simple. Take around 10 grams of hydrolyzed collagen daily with vitamin C, because your body needs vitamin C to make collagen. Bovine collagen has the most joint research behind it. Budget $30-50/month. Add UC-II (40 mg) if you have diagnosed osteoarthritis in any joint.
If You’re a Biohacker or Optimization-Minded
The full stack is BPC-157 + TB-500 + GHK-Cu, cycled. Run BPC-157 and TB-500 for 8-12 weeks, then maintain with GHK-Cu, which also has anti-aging and skin benefits. Use hydrolyzed collagen year-round as a baseline. Demand Certificates of Analysis from your peptide vendor. Here’s how we review vendors. Budget $300-500+/month during active cycles.
If Your Problem Is Knee Pain Specifically
If you’re looking for peptides for knee pain, you’re in the best-studied corner of this whole field. Convenient, because the knee is also the joint that hurts most often.
For the best peptide for knee pain from wear and tear, UC-II has the strongest data among the supplements. The 40 mg trial that beat glucosamine and chondroitin was a knee osteoarthritis trial. The hydrolyzed collagen trials are knee trials too. That is where to start. And if your knees carry extra weight, semaglutide’s STEP 9 trial was a knee osteoarthritis trial as well.
The single human BPC-157 study cited above was also a knee study. Sixteen patients, intra-articular, no placebo arm, self-reported by phone. Promising, not conclusive.
One distinction worth making. If your knee pain is mechanical, meaning a meniscus tear, ligament damage or post-surgical recovery, you are in tissue-repair territory and the BPC-157 and TB-500 logic applies more than the collagen logic. If it is degenerative wear, reverse that order.
If Your Pain Is in a Tendon, Ligament or Another Joint
Shoulder, elbow, hip, ankle, the SI joint, the jaw. Almost every human trial on this page was run on knees, so for anything else you’re guessing from knee data. That matters most for tendons and ligaments, where the case for BPC-157 and TB-500 rests on animal studies. We cover peptides for joints and tendons in more depth in peptides for tendon repair and healing peptides for joints.
If You Have Rheumatoid Arthritis
Worth separating out, because most peptide content lumps rheumatoid arthritis in with osteoarthritis and they are not the same disease.
Osteoarthritis is wear. Rheumatoid arthritis is your immune system attacking the joint lining. A peptide that promotes tissue growth does not address an autoimmune process, and nothing on this page substitutes for disease-modifying treatment.
UC-II is the one with a plausible mechanism here, since oral tolerance is specifically an immune-modulation pathway. Even so, speak to your rheumatologist before adding anything, particularly if you are on immunosuppressants.
5 Misconceptions That Cost People Money and Time
Before you spend a cent, check you’re not making one of these.
Misconception #1: All collagen supplements are the same
They’re not. Type I/III hydrolyzed collagen and Type II undenatured collagen (UC-II) work through entirely different mechanisms. Taking 10,000 mg of hydrolyzed collagen is not a substitute for 40 mg of UC-II, and vice versa. They do different jobs at different doses.
Misconception #2: You’ll feel collagen working in a week
The positive collagen trials ran from 6 weeks to 6 months, and the main UC-II trial measured its result at 180 days. If you quit after three weeks because “it’s not working,” you never gave it a chance. This is the #1 reason people waste money on collagen.
Misconception #3: Higher collagen dose = better results
Nobody has shown that. The knee trials used roughly 3 to 10 grams of hydrolyzed collagen a day, and none tested whether 20 or 30 grams adds anything. For UC-II, the tested dose is 40 mg. Pay for the dose in the trials, not for a bigger number on the tub.
Misconception #4: Peptide injections are dangerous
The safety data on BPC-157 across animal studies is reassuring. In toxicology testing researchers couldn’t reach a lethal dose, even at extremely high doses. The main risks aren’t the peptide itself. They’re source quality and injection technique. Some research peptide vendors sell underdosed, mislabeled or contaminated products. And any injection into a joint carries infection risk. Third-party testing and Certificates of Analysis aren’t optional. They’re the whole ballgame.
Misconception #5: Glucosamine is better studied than collagen
This was arguably true in 2005. It isn’t anymore. Meta-analyses on glucosamine have been increasingly disappointing, with the 2010 BMJ meta-analysis finding no clinically significant benefit over placebo. In the 2016 UC-II trial, glucosamine plus chondroitin didn’t beat placebo either. Meanwhile, collagen peptide trials have been accumulating positive results. The supplement aisle hasn’t caught up to the science.
Is BPC-157 Legal? Status as of September 2026
Short answer. It’s not FDA-approved. It’s no longer blocked from compounding. And it’s not allowed in compounding yet either. Here is how that happened.
- 2023: The FDA placed BPC-157 on its Category 2 list of bulk drug substances, which stopped compounding pharmacies from using it. That is why it has mostly reached people as a “research chemical”.
- 15 April 2026: The FDA removed BPC-157, TB-500, injectable GHK-Cu, KPV and eight other peptides from Category 2.
- 23 July 2026: The FDA’s Pharmacy Compounding Advisory Committee voted 8 to 6 (one abstention) to recommend adding BPC-157 to the list of substances pharmacies may compound. TB-500 and KPV also passed 8 to 6.
- Now: The vote isn’t binding. The FDA still has to propose a rule and take public comment, which legal experts expect to take 12 to 24 months. FDA staff scientists argued against it, citing a lack of quality safety and effectiveness data.
One detail almost nobody mentions. The FDA reviewed BPC-157 for ulcerative colitis and TB-500 for wound healing. Neither was reviewed for joint pain. Until the rule is final, most BPC-157 is still sold as a research chemical, which is why vendor quality is the whole ballgame. And whatever the FDA decides, WADA still bans both for athletes.
How to Buy Peptides Without Wasting Money
For Collagen Supplements
Check four things: type and dose (hydrolyzed collagen at the 3 to 10 g the trials used, or UC-II at 40 mg), source (bovine is most studied), third-party testing (NSF, USP or ConsumerLab verification), and added ingredients (vitamin C is smart, proprietary blends hiding doses are a red flag).
For Research Peptides
This market has real problems. Because BPC-157, TB-500 and GHK-Cu are sold as “research chemicals,” quality control varies wildly.
PeptideRO.org have a guide on peptide vendor comparison.
Certificate of Analysis (CoA) from an independent third-party lab. Not an in-house test. Not a batch number with no lab report. An actual analytical chemistry report from a lab like Janoshik or similar. If a vendor won’t provide this, walk away.
Purity above 98%. Anything below that suggests manufacturing shortcuts or degradation from poor handling.
Proper packaging and storage instructions. Peptides are fragile molecules. Lyophilized (freeze-dried) peptides shipped at room temperature with clear reconstitution instructions are standard. Liquid peptides shipped without cold packs are suspect.
A bad vial doesn’t just waste the money. It wastes the 8 to 12 weeks you spent waiting for it to work.
Going the injectable route? Start with vendors that pass independent testing. See our verified peptide vendors and where to buy BPC-157. Or use the Peptide Finder to match a peptide to your goal.
Peptides for Joint Pain: Frequently Asked Questions
Can peptides help joint pain?
Some can. The best human evidence is for oral collagen. UC-II (40 mg a day) beat placebo and glucosamine plus chondroitin in a 191-person knee trial. Hydrolyzed collagen cut knee pain in a 507-patient meta-analysis. Injectable peptides like BPC-157 have strong animal data but very little human data.
What is the best peptide for arthritis pain?
For knee osteoarthritis, UC-II collagen (40 mg daily) has the best supplement evidence, and hydrolyzed collagen helps too. In people with obesity, semaglutide cut WOMAC knee pain by 41.7 points vs 27.5 on placebo over 68 weeks. For rheumatoid arthritis, talk to your rheumatologist first. No peptide replaces disease-modifying treatment.
What is the best peptide for knee pain?
For wear-and-tear knee pain, start with UC-II (40 mg a day) and hydrolyzed collagen. Both were tested in knee osteoarthritis trials. For a mechanical injury like a meniscus or ligament tear, people usually try BPC-157 and TB-500. But their only human knee data is a 16-patient chart review with no placebo.
Are peptide injections for joint pain safe?
BPC-157 looks safe in animal studies, and a 2-person human IV pilot found no problems at up to 20 mg. The bigger risks are contaminated or underdosed research products and infection, especially with injections into the joint itself. Only buy from vendors with independent Certificates of Analysis. Leave intra-articular injections to a clinician.
What are the 3 peptides for joints?
Usually BPC-157, TB-500 and GHK-Cu, sold together as a “GLOW” blend. BPC-157 plus TB-500 alone is the “Wolverine stack”. No controlled trial has tested either combination. The only human data is 4 knee patients who got BPC-157 plus TB-4, and 3 of them reported relief.
Is BPC-157 legal in 2026?
It’s not FDA-approved. The FDA took it off its Category 2 compounding restriction list on 15 April 2026. In July 2026 an FDA advisory committee voted 8 to 6 to recommend allowing compounding. The FDA still has to finalize a rule, and that’s expected to take 12 to 24 months. WADA bans it for athletes.
Are oral peptides better than injectable peptides for joint pain?
For joint pain, the best human evidence is oral. UC-II and hydrolyzed collagen were tested as daily supplements. BPC-157, TB-500 and GHK-Cu are usually injected because oral absorption for joints is poor or unknown. Try an 8 to 12 week oral course before you consider injections.
How long do peptides take to work for joint pain?
Weeks to months. The collagen trials ran from 6 weeks to 6 months, and the main UC-II trial measured its result at 180 days. Semaglutide’s knee trial ran 68 weeks. Quitting collagen after 3 weeks is the most common way people waste money on it.
Are BPC-157 and TB-500 banned in sports?
Yes. Both are on the WADA prohibited list, banned in and out of competition. There is no therapeutic use exemption for them. Athletes have received 4-year bans. If you compete in a tested sport, don’t use them, whatever the FDA decides about compounding.
What are the best collagen peptides for joints?
Pick by type and dose, not brand. UC-II at 40 mg a day has the best trial for knee osteoarthritis. For hydrolyzed collagen, the trials used 3 to 10 g a day, and bovine collagen has the most joint data. Look for NSF, USP or ConsumerLab testing and skip proprietary blends that hide doses.
The Bottom Line
Joint pain has been managed with band-aids for decades. NSAIDs and cortisone quiet the pain. Glucosamine barely beats placebo. None of them rebuild anything. Peptides try a different approach. They signal repair instead of masking pain.
Collagen peptides (both hydrolyzed and UC-II) have the strongest human evidence among supplements, the safest legal status and the lowest cost. They should be the foundation for anyone with joint pain. If you’re not already taking a full dose of hydrolyzed collagen daily, that’s the single highest-ROI change you can make.
If your weight is part of the picture, semaglutide has the biggest joint-pain trial of any peptide. That’s a prescription conversation, but it’s worth having.
BPC-157 has the most interesting mechanistic data and anecdotal support of any research peptide for joint repair. The one human knee study found 11 of 12 patients reported improvement, but it had no placebo and relied on phone self-reports. The evidence base is still young, the legal status is in transition, and source quality is a real concern. If you go this route, take it seriously. Use a vendor with third-party testing and follow established protocols.
The Wolverine Stack (BPC-157 + TB-500) is the community’s favorite for good reason, but “community favorite” isn’t the same as “clinically validated.” The logic of combining localized repair with systemic anti-inflammatory action is sound. The evidence is 4 patients and a lot of anecdotes.
GHK-Cu is the underrated option with interesting science behind it. As your natural GHK-Cu levels decline with age, supplementing may address a real physiological deficit.
Start with what’s proven. Add what’s promising. Track your results. And be honest with yourself about what’s working and what isn’t.
Not sure where to start? Put your joint and your goal into the Peptide Finder and get a shortlist.
Your joints didn’t break overnight. Fixing them won’t happen overnight either. But with the right combination of evidence-based peptides, realistic expectations, and a protocol you actually stick to, the trajectory can change.
References
- Lugo JP, Saiyed ZM, Lane NE. Efficacy and tolerability of an undenatured type II collagen supplement in modulating knee osteoarthritis symptoms. Nutrition Journal, 2016. PMC4731911
- Lin CR et al. Analgesic efficacy of collagen peptide in knee osteoarthritis: a meta-analysis of randomized controlled trials. Journal of Orthopaedic Surgery and Research, 2023. PMC10505327
- Efficacy and safety of low-molecular-weight collagen peptides in knee osteoarthritis: a randomized, double-blind, placebo-controlled trial. Frontiers in Nutrition, 2025. doi:10.3389/fnut.2025.1644899
- Gupta A, Maffulli N. Undenatured type II collagen for knee osteoarthritis. Annals of Medicine, 2025. PMC12010644
- Yuenyongviwat V et al. Efficacy of combined undenatured type II collagen and hydrolysed collagen supplementation in knee osteoarthritis: a randomised controlled trial. Scientific Reports, 2025. PMC12405528
- Bliddal H et al. Once-weekly semaglutide in persons with obesity and knee osteoarthritis (STEP 9). New England Journal of Medicine, 2024. doi:10.1056/NEJMoa2403664
- Lee E, Padgett B. Intra-articular injection of BPC 157 for multiple types of knee pain. Alternative Therapies in Health and Medicine, 2021. PMID 34324435
- Safety of intravenous infusion of BPC157 in humans: a pilot study. Alternative Therapies in Health and Medicine, 2025. PMID 40131143
- Matek et al. Tendon, ligament, and muscle injury therapy perspectives with growth factors and stable gastric pentadecapeptide BPC 157: a review. Pharmaceuticals, 2026. PMC12944561
- Wandel S et al. Effects of glucosamine, chondroitin, or placebo in patients with osteoarthritis of hip or knee: network meta-analysis. BMJ, 2010. doi:10.1136/bmj.c4675
- U.S. FDA. Pharmacy Compounding Advisory Committee meeting, July 23-24, 2026. fda.gov
- USADA. BPC-157: experimental peptide creates risk for athletes. usada.org
- TPX-100 Phase 2 results, OARSI World Congress 2022, reported by Healio. healio.com
This article is for informational and educational purposes only. It is not medical advice. Research peptides like BPC-157, TB-500 and GHK-Cu are not FDA-approved for human use. Consult a qualified healthcare provider before starting any peptide protocol or supplement regimen, especially if you have existing medical conditions or take medications.